
The Brain's Pain Dial: Why the Same Stimulus Can Hurt Differently From Person to Person
A paper cut hurts more during an argument than on a quiet Sunday morning. The wound is identical. The pain is not. Research into how the brain modulates pain signals explains why — and the answer is more surprising than most people expect.
Imagine two paper cuts. Same finger, same depth, same amount of tissue damage. One happens on a quiet Sunday morning with nothing else on your mind. The other happens in the middle of a heated conversation. Most people will tell you, without hesitating, that the second one hurt more.
The wound is identical. The pain is not. This is not an illusion or a matter of character — it reflects something specific about how the brain processes pain signals. Pain is not a fixed readout of tissue damage. It is a judgment the brain makes, and like many judgments, it can be influenced by context, expectation, attention, and the state of neural circuits that most people have never heard of.
The research into those circuits has grown substantially in recent years. Understanding what is known — and where the evidence runs out — changes how pain makes sense.
The Brain's Descending Traffic — Amplify or Suppress?
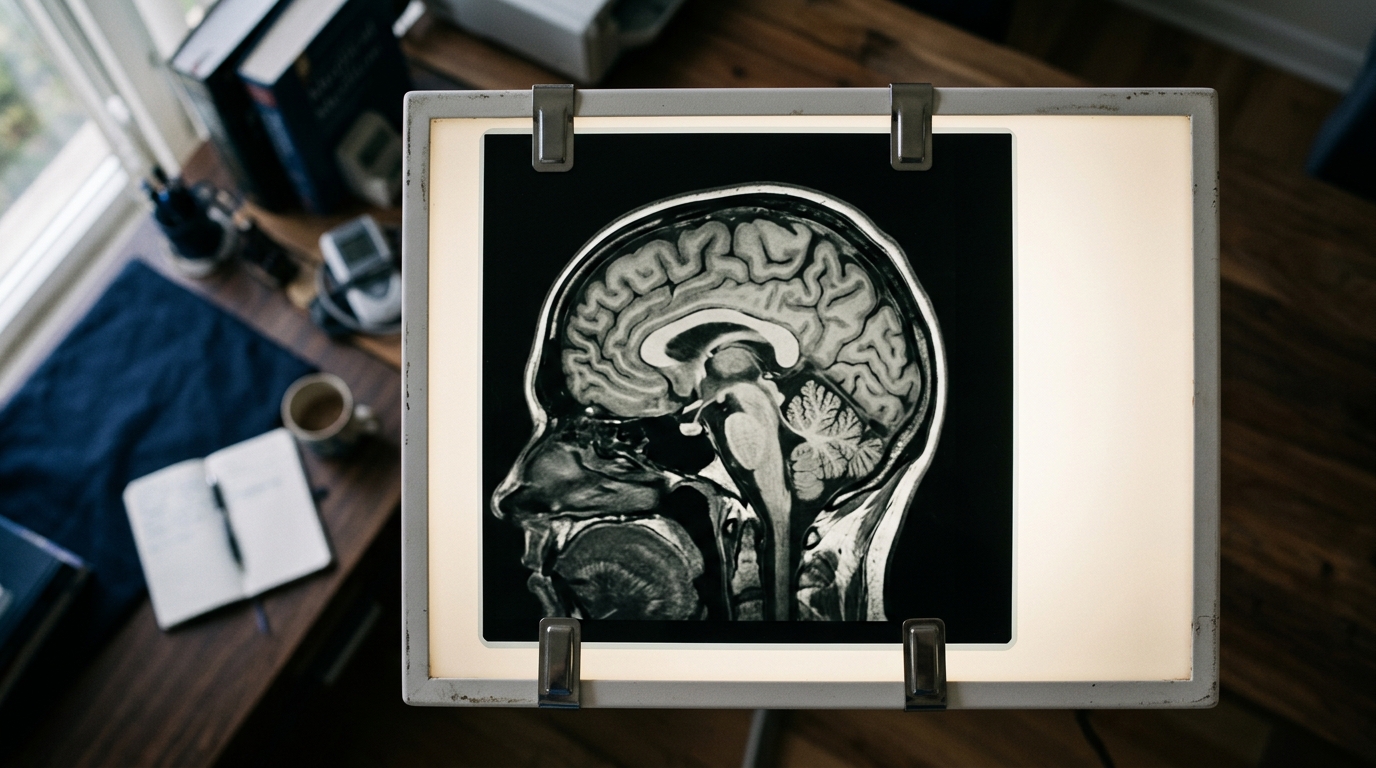
Pain signals do not travel in one direction. Tissue sends a signal upward through the spinal cord and brainstem toward the cortex, but the brain simultaneously sends signals back down, and those descending signals can either quiet the incoming message or turn it louder. This bidirectional architecture — descending pain modulation — is where a great deal of pain variability lives.
Two structures sit at the center of the descending system: the periaqueductal grey (PAG), a region in the midbrain, and the rostral ventromedial medulla (RVM), a cluster in the brainstem. Together, they act as a relay station that can send either inhibitory or facilitatory signals to the spinal cord, changing how much of the original pain message reaches conscious awareness. A 2026 review by D’Souza and colleagues in Frontiers in Pain Research documented this pathway in detail, describing the PAG-RVM axis as the primary anatomical substrate for descending control.
But the descending system does not operate in isolation. Cortical regions — including the prefrontal cortex, anterior cingulate cortex, insula, and amygdala — connect to and influence the PAG-RVM relay. These are the regions most involved in attention, emotional processing, threat appraisal, and decision-making. Their involvement explains a great deal. Distraction, for example, tends to activate inhibitory pathways — the brain turns the incoming signal down because resources are allocated elsewhere. Anxiety and sustained threat appraisal, by contrast, tend to activate facilitatory pathways — the brain amplifies the signal because the context flags it as important (D’Souza et al., 2026).
This is not a metaphor. It is anatomy. The same peripheral input passes through a neural circuit that is continuously shaped by what the brain is doing with attention, emotion, and prediction. Context is not an overlay on top of pain — it is part of the mechanism that produces it.
What Expectation Does to the Signal
One of the most direct tests of how the brain shapes pain comes from research on expectation — specifically, the nocebo effect. A nocebo effect occurs when negative expectation increases experienced pain or worsens an outcome, in the same way a placebo effect does the reverse. The question researchers have been investigating is whether the two are symmetric: does believing something will hurt more produce as strong an effect as believing it will hurt less?
A 2025 preregistered randomized controlled trial published in eLife (Babel et al., 2025) measured this directly in 104 healthy volunteers. Participants received an experimental pain stimulus — standardized heat applied to the forearm — under different expectation conditions. The key finding: nocebo effects on pain intensity were significantly larger than placebo effects. Believing the stimulus would hurt more produced a stronger shift in reported pain than believing it would hurt less, and crucially, the nocebo effect was still detectable one week later during a follow-up session. The placebo effect was not.
The researchers proposed that this asymmetry reflects an evolutionary logic. The brain is wired to weight threat signals more heavily than safety signals — a bias known as negativity bias — because under conditions of genuine danger, underestimating pain is more costly than overestimating it. This means that when expectation shapes pain, the direction of expectation matters enormously.
For people in pain, this has a practical implication that the researchers noted carefully: negative information about a painful procedure or condition may have stronger and more lasting effects on experienced pain than positive information, even when both are delivered with the same clinical intent. That is not a reason to withhold accurate information — it is a reason to understand that how information lands in the nervous system is not neutral.
How Much the Inhibitory System Varies Between People
If the descending modulation system can quiet incoming pain signals, a natural question follows: does it work equally well in everyone? The research answer is no — and the degree of variation is substantial.
Conditioned pain modulation (CPM) is a clinical test designed to measure how well the descending inhibitory system functions. In the standard protocol, an individual rates pain from a test stimulus (typically mild heat or pressure), then receives a second, more intense conditioning stimulus, and then rates the test stimulus again. In most people, the second rating is lower — the conditioning stimulus has activated descending inhibition, and the test stimulus hurts less. The size of that reduction is the CPM effect.
A 2026 multi-site study by Petersen and colleagues in the European Journal of Pain reported the CPM effect across a large combined sample with careful attention to measurement reliability. The average effect size was approximately d = 0.52 to 0.54 — a medium effect by statistical convention, meaning CPM produces a meaningful inhibitory response on average. Test-retest reliability was good (ICC = 0.73–0.77), suggesting the measure captures something stable about an individual’s nervous system.
But the 95% confidence intervals around the individual-level effects told a different story. A meaningful subset of participants showed net facilitation rather than inhibition — their pain ratings after the conditioning stimulus went up, not down. This is not measurement noise. It indicates that for some individuals, the descending system amplifies rather than suppresses under conditions designed to activate inhibition.
This finding has direct relevance to why two people can respond so differently to the same painful stimulus. The inhibitory capacity of the descending system varies across the population in ways that a group-level average conceals. Petersen et al. (2026) were explicit that the population-level CPM effect cannot predict the response of any individual.

When the System Amplifies — What Chronic Pain Research Has Found
The individual variation in CPM documented in healthy populations becomes more pronounced in chronic pain conditions. Fibromyalgia is the condition in which the relationship between descending inhibition and amplified pain has been studied most extensively, and the findings have reshaped how researchers think about chronic widespread pain.
A 2025 review by Carneiro and colleagues in Diagnostics documented that fibromyalgia is consistently associated with a deficient CPM response. Where healthy controls show inhibition in response to a conditioning stimulus, many people with fibromyalgia show flat or even facilitatory responses. The descending system is not turning down the incoming signal. In some cases, it may be adding to it.
Carneiro et al. (2025) described this as a measurable biomarker of central amplification — the point at which pain processing shifts from a normal response to injury or threat toward a state in which the nervous system itself has become a source of amplification. The term for this shift is central sensitization: a state in which the central nervous system’s response to incoming signals is heightened beyond what the peripheral input alone would produce.
A 2026 scoping review by Owolabi-Akintola and colleagues in Frontiers in Pain Research extended this picture. The review found that the chronification of pain — the process by which acute pain transitions to persistent pain — involves changes in both ascending sensitization and descending modulation circuitry. Cortical reorganization and altered coupling between prefrontal regions and the limbic system were documented across multiple chronic pain conditions, not only fibromyalgia. The authors described a feedback loop in which amplified signals reinforce the neural architecture that produces amplification (Owolabi-Akintola et al., 2026).
This framework does not mean that chronic pain is “in someone’s head” in the dismissive sense of that phrase. The changes are measurable, physiological, and affect the architecture of the central nervous system itself.
What the Research Does Not Yet Establish
The science reviewed here is substantial — but its limits are worth naming plainly.
CPM protocols vary across laboratories in ways that affect results. The type of conditioning stimulus, its duration and intensity, and the timing between conditioning and test measurements all influence the measured effect. Petersen et al. (2026) conducted a multi-site study partly to quantify this variability, and they found meaningful differences across sites even when protocols were standardized. What this means in practice is that CPM scores reported in different studies may not be directly comparable, and individual CPM measurements in clinical settings carry uncertainty that group-level effect sizes do not fully convey.
The nocebo research from Babel et al. (2025) was conducted in healthy volunteers using experimental pain under controlled laboratory conditions. Laboratory pain and clinical pain differ in important ways — duration, emotional context, personal meaning, and prior history with pain. Whether the nocebo asymmetry observed in healthy volunteers applies in the same magnitude to people with chronic pain conditions has not been established by this study.
The case that the brain actively constructs pain rather than merely reporting it is well-supported in the current literature. But this finding has sometimes been misused to suggest that people with chronic pain are experiencing something primarily psychological. The research does not support that conclusion. Central sensitization and altered descending modulation are physiological changes in nervous system function — describing them in neural terms does not diminish the reality of the pain they produce.
Finally, knowing that expectation, context, and descending inhibitory capacity shape pain does not, on its own, indicate what can be done to change any of these factors. That question remains a focus of active research.
Frequently Asked Questions
Is pain always proportional to how much tissue damage there is?
No. While severe injury generally produces more pain than minor injury, the correspondence is not reliable at the individual level. People with identical injuries often report very different pain intensities, and people can experience significant pain with no detectable tissue damage. Research into descending pain modulation explains part of why: the brain’s processing of incoming pain signals is shaped by context, expectation, attention, and the state of inhibitory circuits — not only by the peripheral signal itself.
What is the periaqueductal grey, and what does it do?
The periaqueductal grey (PAG) is a region in the midbrain that serves as a key hub in the brain’s descending pain modulation system. It connects to the rostral ventromedial medulla (RVM) in the brainstem, and together these two structures can send signals down the spinal cord that either reduce or amplify incoming pain messages. The PAG receives input from cortical regions involved in attention, emotion, and threat appraisal, which is why psychological and cognitive states can influence pain intensity through a physiological pathway.
What is conditioned pain modulation (CPM)?
Conditioned pain modulation (CPM) is a clinical measurement of how effectively the brain’s descending inhibitory system suppresses pain. A researcher applies a painful test stimulus and measures the response, then applies a second, more intense conditioning stimulus, and measures the test stimulus response again. In most people, the test pain is lower after the conditioning stimulus because the conditioning has activated descending inhibition. The difference between the two ratings is the CPM effect. Research has found considerable variation in CPM across individuals, including some people who show net facilitation rather than inhibition.
Why are nocebo effects — expecting more pain — stronger than placebo effects?
A 2025 preregistered study in eLife (Babel et al., n=104) found that nocebo effects on experimental pain were significantly larger than placebo effects and persisted at a one-week follow-up while placebo effects did not. The researchers proposed that this asymmetry reflects the brain’s tendency to weight threat signals more heavily than safety signals — a bias that may have evolutionary origins. When the brain anticipates harm, that expectation appears to have a stronger influence on the pain-processing system than an expectation of reduced harm.
What is central sensitization?
Central sensitization is a state in which the central nervous system’s response to incoming pain signals becomes heightened beyond what the peripheral input would produce on its own. Rather than reflecting ongoing tissue damage, the amplified pain reflects changes in how the nervous system itself processes signals. Research in fibromyalgia has documented measurable CPM deficits associated with central sensitization. A 2026 scoping review found that the transition from acute to chronic pain involves changes in both ascending sensitization and descending modulation circuitry across multiple conditions — not only fibromyalgia.
Sources
- D'Souza C et al. (2026). A review of descending pain modulation in humans. Frontiers in Pain Research — Frontiers in Pain Research
- Carneiro BD et al. (2025). Descending Pain Modulation in Fibromyalgia. Diagnostics (MDPI) — Diagnostics (MDPI)
- Babel P et al. (2025). Nocebo effects are stronger and more persistent than placebo effects in healthy individuals. eLife — eLife
- Owolabi-Akintola Y et al. (2026). Contemporary evidence for CNS mechanisms underlying chronic pain. Frontiers in Pain Research — Frontiers in Pain Research
- Petersen KK et al. (2026). Conditioned Pain Modulation Inter-Site Variability Study. European Journal of Pain — European Journal of Pain
Understand Your Nervous System
Understanding how the nervous system regulates signals — including pain, stress, and arousal — is central to brain health. If you are curious about your own nervous system's regulatory patterns, our team offers a no-cost initial consultation to explore what assessment and support might look like.
Schedule Your Free Consultation
Call us: (424) 625-5445 · Los Angeles, CA
Disclaimer: This content is for informational purposes only and does not constitute medical advice, diagnosis, or treatment. LENS Neurofeedback is not FDA-approved for all conditions mentioned. Please consult with a qualified healthcare provider before beginning any new treatment program.

A balanced brain is a better brain for a happier life.